
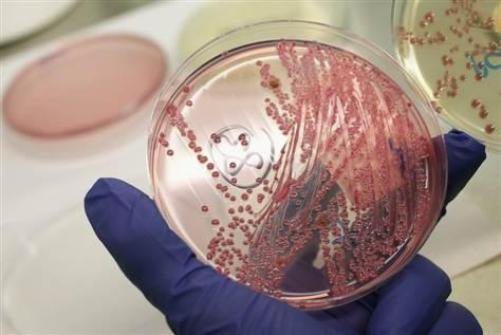
Gonorrhea (Neisseria gonorrhoeae) is a sexually transmitted infection (STI) that has been with us for a long time. There are descriptions of conditions that fit with gonorrhea — penile burning, discharge and scarring — dating as far back as biblical times. Whether those descriptions were actually gonorrhea or not is not possible to know as the bacteria that causes gonorrhea was not identified until 1879, but as approximately 80 to 85 percent of men with gonorrhea develop symptoms these historical descriptions, also recounted by ancient Greek physicians, do fit.
Over the centuries there have been a variety of therapies to treat the infection and its complications, many of which are too horrible and graphic to describe here. The therapies were also largely ineffective. And so men and women suffered severe complications of an untreatable bacterial infection that caused abscesses and scarred the reproductive tract. That suffering came to and end with the introduction of antibiotics in the 1940s.
Or so we thought.
Gonorrhea, it turns out, has a unique ability to develop resistance to antibiotics. Since I have been in medicine — about 30 years — we have gone though four major classes of antibiotics for the treatment of gonorrhea. All worked well initially, but medically speaking for a frighteningly short period of time. Antibiotic resistance is never unexpected, but developing it this quickly and efficiently is alarming.
And now we are left with few options. A two-drug combination: an injection of the antibiotic ceftriaxone given with an oral antibiotic called azithromycin. The idea behind the two drug cocktail is to hopefully limit the development of antibiotic resistance. Unfortunately, almost 20 percent of people treated for gonorrhea in 2016 were not treated according to these guidelines, which may increase the risk of gonorrhea resistance.
Being limited to one antibiotic combination is bad enough, but we are also faced with rising rates of gonorrhea. In 2017, over 500,000 cases of gonorrhea were reported to the Centers for Disease Control and Prevention (CDC) — this is largest number since 1991 and almost 20 percent more cases than in 2016. Rising rates of an infection with limited therapies that is known to rapidly develop antibiotic resistance is not good. There is no other way to describe it.
There are already cases of highly resistant gonorrhea, meaning the antibiotic combination of ceftriaxone and azithromycin has been ineffective.
Left untreated both gonorrhea can cause pelvic inflammatory disease (PID), a serious infection of the uterus and fallopian tubes for women. Consequences include infertility, ectopic (tubal) pregnancies and chronic pelvic pain. Men can develop scaring of the urethra as well as infertility. Both men and women with gonorrhea are at risk of developing serious blood stream infections, and babies exposed to gonorrhea at birth can develop blindness as well as a blood stream infection. Even when there are no symptoms or serious complications simply being infected with gonorrhea increases the likelihood of contracting HIV (human immunodeficiency virus) if exposed.
This week the New England Journal of Medicine published a glimmer of hope — a study looking at a new antibiotic called Zoliflodacin, which was effective for treating gonorrhea in the genital tract and rectum (less so for oral infections). It’s a start, but we need a lot more research like this, especially given gonorrhea’s track record with antibiotics.
What can you do?
 Insist on condoms, male or female, when you are unsure of your partner’s status for gonorrhea or if you are in non-monogamous relationship. Don’t assume gonorrhea happens to “other people.” STIs are the great and unfortunate equalizer.
Barrier protection for oral sex is just as important. Oral sex is a efficient way for both men and women to catch the infection, and oral infections can be harder to treat.
If you are in a higher-risk group, for example women under the age of 25, men who have sex with men and anyone in a non-monogamous relationship, get tested for gonorrhea.
If you test positive for gonorrhea, make sure you receive two antibiotics not one.
Press your elected officials to make funding for antibiotic research a priority.
Otherwise, we are going to find ourselves in medieval times with gonorrhea, medically speaking, and the prospect of not having ways to treat this infection is frightening.
Dr. Jen Gunter is a Marin resident and an ob/gyn in San Francisco. Her column appears every fourth week.